Tuesday, November 9, 2010

Acute Hepatitis

Today we discussed a case of acute hepatitis NYD with moderate-severe liver enzyme elevation. This is not an uncommon referral to Internal Medicine.

Here's a very useful review from CMAJ in 2005 on elevated liver enzymes.

Some points about marked liver enzyme elevation (>5x the upper limit of normal):

1. Remember that the "liver function tests" are bilirubin, INR, albumin +/- glucose and can reflect the synthetic function of the liver. Conversely, the "liver enzymes" - AST, ALT, ALP and GGT are NOT liver function tests as they offer no information on the liver's synthetic function but merely are a marker of hepatocyte integrity and/or cholestasis.

2. The differential diagnosis of moderate to severe transaminitis includes: viral hepatitis, toxic hepatitis, ischemic hepatitis, severe obstruction, autoimmune and alcoholic hepatitis.

3. Decide what the predominant pattern is to help you guide investigations:
a) Hepatic (increased AST, ALT > ALP)
b) Cholestatic (increased ALP > AST, ALT)

4. How elevated are the enzymes? 5x vs. 5-10x vs. >10x of normal? What is the trend? Is there synthetic dysfunction (increased INR, bilirubin, decreased albumin)? Typically liver enzyme values at this level represent acute liver injury.

5. In acute viral hepatitis, the liver enzymes often peak before the bilirubin and the patient may have non-specific symptoms such as fatigue, arthralgias and a low grade fever (as in our patient) .

6. Consider ischemic hepatitis in the right clinical context and an ALT/LDH ratio of less than 1.

7. Hepatitis screen: Hep A IgM Ab, Hep B core Ab (IgM), Hep B surface Ag and Ab, Hep C Ab.

8. Always ask about Tylenol use, herbal and over the counter medications, periods of illness (hypotension), autoimmune symptoms and alcohol.

9. Some form of abdominal imaging (usually ultrasound) is often appropriate to assess for evidence of hepatitis and/or obstruction.

10. Once the common causes of moderate to severe transaminitis have been ruled out, consider testing for auto-immune hepatitis and other viral causes such as EBV and CMV.


Monday, November 8, 2010

Knee Pain

Yesterday we talked about the diagnostic dilemma of a painful knee that ultimately was presumed to be secondary to osteoarthritis.

This a good opportunity to review the approach to an acute monoarthritis and to osteoarthritis.

Let's start with some Canadian content. Here's a recent review published in the CMAJ looking at the management of a patient with an acute monoarthritis.

The NEJM published a very thorough review article on OA of the knee in 2006.

There are many causes of knee pain outside of a monoarthritis or osteoarthritis, many of which we do not see very often as internists (i.e. orthopedic problems in younger patients).


To summarize, here are some key points on evaluating a patient with acute knee pain:

1. Determine if there is a recent history of trauma. This raises the pre-test probability of a fracture, hemarthrosis, meniscal tear or ligamentous injury.

2. Decide whether this is an intra-articular, peri-articular or referred process (there is significant overlap in some of these signs/symptoms):

a) Intra-articular: pain localized to the knee without radiation, knee effusion, mechanical symptoms (clicking, locking, giving way), abnormal structural physical exam, reduced range of motion.

b) Peri-articular: focal area of pain or abnormalities on exam, pain only during parts of the range of motion, +/- mechanical symptoms.

c) Referred pain: vague location of pain, back or hip pain, pain not exacerbated by knee movement, lack of an effusion, normal knee exam.

3. If the pain is articular, you need to decide if it is inflammatory (i.e. arthritis - pain, redness, swelling, warmth) or non-inflammatory (structural). Any acute effusion should be drained and analyzed.

4. Remember if an effusion is present -> rule out INFECTION. Missing a septic joint can have catastrophic consequences for the joint, and very quickly.

5. Arthrocentesis fluid should be sent for cell count and differential, gram stain, C&S, microscopy for crystals at a minimum.

6. Imaging: Start with x-rays. If there is any history of trauma, lack of localizing symptoms to the knee or a question of pain origin, image the ipsilateral joints above and below the knee.

7. Consider MRI as the next imaging test of choice after x-ray if no diagnosis can be found or if a soft tissue etiology is being considered.

8. An effusion can be present in an acute exacerbation of osteoarthritis.


Friday, November 5, 2010

Renal Cell Carcinoma

Today we talked about renal cell carcinoma presenting with anorexia, abdominal distension, hematuria, ascites and renal failure.

Here are links to two review articles, the first is from the Lancet in 2009 and the second is from NEJM in 2005.

Some key points about RCC:

1) RCC is the 7th most common cancer in men and the 9th most common in women. The peak incidence is in the 6th and 7th decades of life (mean age of 60). Men are affected twice as frequently as women.

2) Risk factors include: HTN, obesity, smoking, acquired cystic diseases of the kidney, ESRD and certain inherited conditions (e.g. von Hippel-Lindau). Regardless, most patients with RCC do not have an identifiable risk factor. Fruit and vegetable consumption may be protective!

3) This tumor was classically known as "The Internist's Tumor" due to its varied presentation, however with the widespread use of abdominal imaging and incidental diagnosis, some argue that RCC is now "The Radiologist's Tumor".

4) Signs and Symptoms at Presentation:
a) Local: The classic triad of abdominal pain, a palpable mass and hematuria is uncommonly seen today.
b) Systemic: Anorexia, fatigue, wasting and a variety of paraneoplastic phenomena including hypercalcemia (PTHrp), HTN (renin) and erythrocytosis (EPO).

5) Any patient over the age of 40 with hematuria should be assessed for RCC since prognosis is determined by stage.

6) Imaging: CT abdomen is the investigation of choice. However, abdominal U/S while less sensitive can help differentiate a simple cyst from a more complex structure. MRI can be useful if the U/S is non-diagnostic or contrast dye is contraindicated.

7) If a solid renal mass is identified with radiologic features consistent with RCC, biopsy is usually not performed due to low specificty and concern with seeding the peritoneum. Good surgical candidates often go directly for a partial or radical nephrectomy.

8) Surgical resection is the cornerstone of therapy as chemotherapy is minimally effective. Surgery can be curative in the majority of patients with Stage I, II and III disease. Resection of the primary tumor is recommended even in the setting of metastatic disease (in patients with good functional status).

9) Significant interest is currently focused on biologic agents including VEGF and mTOR inhibitors given the limited benefit and significant toxicity of Interleukin-2 immunotherapy.

Thursday, November 4, 2010

The Art of Pimping

Hi folks,

Usually we keep things pretty formal and academic here on Horses and Zebras, but today we're going to talk about something different - the art of pimping.

For those unfamiliar with the term as it applies to Medicine, this is when a staff "poses a series of very difficult questions to an intern or student." Often this is done to further learning or highlight gaps in knowledge, but at times it can make the learner feel self-conscious or even uncomfortable.

We've all experienced this and part of going through your training is knowing how to handle it.

Check out the very humorous, but all too true article that started it all. Some excellent defensive tips are offered.

Our own Dr. Detsky furthered the discussion on this topic with his article from JAMA in 2009.

In all seriousness, "pimping" will continue to be a part of medical education for the foreseeable future. Here are some things (from one trainee to another) that have helped get me though the 10,000 times I've been put on the spot:

1) Remember that your staff is trying to help you learn, not hurt your feelings. You will never forget something you got wrong when pimped (i.e. the Toronto clinical prediction rule for aortic stenosis).

2) It's OK to stop, take a deep breath and think about the answer rather than blurting out the first thing that comes to mind.

3) If you don't know the answer or are never going to remember it, just be honest and say, "I don't know." This is better than squirming for 5 minutes during which time it'll be obvious you didn't know the answer.

4) If you think you know the answer, then answer with confidence. Not arrogance, but confidence. If you're right, you'll get credit for being right! If you're wrong - you were going to be wrong anyway, so you've lost nothing. However, if you're right but you answered in a sheepish, high pitched and uncertain voice, you'll only get credit for guessing.

Finally, when it's your turn to be the teacher, remember what it felt like to get "pimped".

Wednesday, October 27, 2010

Chronic Diarrhea


Today we talked about a patient with chronic diarrhea.

Here is a useful review article from Gastroenterology in 2004.

Guidelines from the American Gastroenterology Association were published in 1999.

Working up chronic diarrhea can be challening as the differential diagnosis is quite broad, clinical trials are lacking and expert opinion is varied.

Some key points:

1) Chronic diarrhea is not well defined. A reasonable definition might be:

  • Decrease in stool consistency ("stool that takes the shape of the vessel it is in")
  • >3 stools and/or >200g of stool per day
  • >4 weeks duration

2) Have an organized approach to the types of chronic diarrhea (which leads to the differential). The guidelines suggest watery vs. inflammatory vs. fatty. Another classification scheme includes secretory vs. malabsorption/osmotic vs. inflammatory.

3) Use the history and physical exam to direct your initial set of investigations. Make sure to take a good medication and travel history!

4) Reasonable initial tests beyond the routine:

  • Stool osmotic gap [290 - 2(stool Na + stool K)] and pH
  • FOBT
  • TSH
  • anti-TTG and IgA level (if risk factors for celiac)
  • Stool C&S, O&P (repeat over several days) and C.diff
  • Fecal WBCs
  • Response to fasting
  • +/- 72 hour fecal fat testing (difficult to get done)
  • +/- Colonoscopy or Sigmoidoscopy
  • +/- Abdominal imaging

5) Stool osmotic gap (see above):

  • a value less than 50 suggests secretory diarrhea (i.e. lots of secreted electrolytes in the lumen)
  • a value greater than 125 suggests osmotic diarrhea (i.e. lots of unmeasured osmoles in lumen)
  • values in between are indeterminate

6) Testing for pancreatic insufficiency, bacterial overgrowth, hormone levels (gastrin, calcitonin, VIP, carcinoid), mucosal abnormalities, etc. can be pursued as appropriate following the initial set of investigations.

7) Some authors suggest that more than 80% of chronic diarrhea cases have a treatable etiology.

Tuesday, October 26, 2010

Hemoptysis

Hey folks,

Horses and Zebras is back after a brief absence!

Today we talked about a patient with new onset hemoptysis and an otherwise normal physical exam, screening blood work and CXR.

Here's a short and focussed review article from AFP on hemoptysis. It includes a very easy to follow algorithm and a good differential diagnosis.

A couple of key take-home points:

1) Always start with the ABCs. While we worry about dropping hemoglobin and hypotension, remember that one of the biggest risks in patients with hemoptysis is airway compromise and hypoxia.

2) Decide if this is actually hemoptysis! Blood from the GI tract or above the vocal cords (pseudohemoptysis) can mimic hemoptysis.

3) Infection and cancer are the most common diagnoses.

4) Evaluate for massive hemoptysis (>200-600cc/24 hours). This may suggest a diagnosis but also implies a much higher risk of airway compromise and need for aggressive airway management.

5) Reverse the reversible - correct coagulopathies, thrombocytpenia, etc.

6) After routine bloodwork - get a CXR. Go on to bronchoscopy or a high resolution CT scan of the chest in patients with massive hemoptysis, persistent bleeding, CXR findings or risk factors for lung cancer.

7) Call for help sooner rather than later - ICU, respirology, thoracic surgery - if the bleeding is not resolving or is getting worse. Specialized airway skills may be needed.

Friday, September 17, 2010

Multiple Myeloma


Today we discussed a classic case of Multiple Myeloma with hypercalcemia, renal failure, anemia, and bone pain secondary to lytic bone lesions... these features make up the mnemonic CRAB: hyperCalcemia, Renal failure, Anemia, Bone pain.

Here is a link to a previous Horses & Zebras blog summarizing the Clinical Features of Multiple Myeloma, as well as some links to articles reviewing investigation and management of hypercalcemia and current management options for multiple myeloma.

Management of hypercalcemia +/- acute renal failure is often the primary problem that needs to be managed on admission to hospital. Hypercalcemia can be considered to be mild (2.6 - 2.9 mmol/L), moderate (3.0 - 3.4 mmol/L), and severe (greater than 3.5 mmol/L); however, there are no official cut-off points for hypercalcemia. As we discussed this morning, ~40% of calcium is bound to albumin and thus low albumin states will lower the measured calcium. This can be corrected roughly by adding 0.2 mmol/L to a calcium measurement for every drop in albumin of ~10.

Treatment of Hypercalcemia

1. First line treatment for hypercalcemia is fluid resuscitation, as the majority of patients will be volume contracted. Rapid, aggressive resuscitation is the goal, monitoring for any potential volume overload/heart failure in susceptible patients.

2. Administration of an IV bisphosphonate is also considered appropriate in severe hypercalcemia. Pamidronate (60 - 90 mg) is the usual choice, given once over 2-4 hours, and most often normalizing calcium within 5-7 days.

3. For more immediate calcium-lowering calcitonin can be considered; however, it is not uncommon for patients to develop tachyphylaxis and thus its use is limited.

4. Alternatively, and often more effective in the setting of lymphoma or multiple myeloma induced hypercalcemia, glucocorticoids such as prednisone (1 mg/kg daily) can be considered.

5. Management of hypercalcemia always includes investigation into the underlying cause, and treatment of such problem otherwise the hypercalcemia will recur.

Friday, September 10, 2010

Guillain-Barre Syndrome

This week we explored 2 different (potential) cases of Guillain-Barre Syndrome, or GBS. First during Physical Examination Rounds and then again in Morning Report.

The most common form of GBS is an idiopathic acute inflammatory demyelinating polyneuropathy (AIDP), and in fact GBS is often synonymous for AIDP. It is an autoimmune process directed against Schwann cell membranes. There are 5 other variants of GBS, including the Miller Fisher Variant which often presents with the triad of ophthalmoplegia, ataxia, and areflexia.

GBS occurs anywhere from 1 - 2 per 100,000 per year. It is often (~2/3 of cases) preceded by either a respiratory or GI infection, most commonly Campylobacter. GBS has also been reported after vaccinations and to be associated with systemic illnesses, such as SLE, Hodgkin's Lymphoma, Sarcoidosis, etc.

Patients with GBS often present with parasthesias in their limbs, followed soon after by ascending weakness. This progresses over days to weeks. GBS can also be associated with autonomic dsyfunction such as orthostasis, urinary retention, constipation, and tachycardia.

Physical examination most often reveals symmetrical motor weakness in an ascending pattern, with absent reflexes, flaccid tone, and a normal sensory exam.

Patients with GBS need to be monitored closely for respiratory failure due to involvement of the diaphragm. A good rule of thumb for consideration of intubation is the 20/30/40 rule:
  • 20: Vital Capacity less than 20 cc/kg
  • 30: Maximum Inspiratory Pressure less than 30 cm H2O
  • 40: Maximum Expiratory Pressure less than 40 cm H2O

Treatment for GBS is most often supportive, and may require an ICU setting for ventilatory support, hemodynamic support, nutritional support, and pain control. If diagnosed within the first 4 weeks then IVIG or plasmapheresis can be considered. A recent Cochrane review suggests that IVIG treatment has similar outcomes to plasmapheresis in the setting of early (ie: within 2 weeks) diagnosed GBS.

Outcomes for patients with GBS are quite good with ~80% achieving full recovery within a few months to a year; however, minor deficits often persist. 5-10% will have permament disabling deficits, and another 2-3% will die as a result of their GBS. Approximately 5-10% of patients may develop one or more relapses of their GBS, leading to a diagnosis of Chronic Inflammatory Demyelinating Polyneuropathy (CIPD).

Here is a very thorough review of GBS from 2005, in The Lancet.

Friday, September 3, 2010

Pulmonary Hypertension


Today we discussed a case of newly diagnosed Pulmonary Hypertension in a young woman.

Pulmonary Hypertension (PH) is defined as a Pulmonary Arterial Pressure over 25 mmHg at rest (normal 12-16 mmHg).

Patients often present with months or years of gradually progressive symptoms, such as shortness of breath, fatigue, cough, angina, peripheral edema, and rarely hemoptysis.

Cardiovascular examination often reveals a loud, palpable P2, a split S2, and an RV heave.

There are multiple causes of PH, but all result in increased pressures within the pulmonary vasculature, either due to vasoconstriction of the blood vessels, obstruction by way of a mass or pulmonary emboli, or fibrosis within the lung parenchyma related to systemic illnesses. In order to overcome this increased pulmonary pressure, the heart then is required to create elevated right-sided pressures in the heart. In turn, this leads to RV hypertrophy and potentially RV failure.

PH is classified according to the WHO into 5 major categories:
Class I: Pulmonary Arterial Hypertension
  • Idiopathic
  • Familial
  • Connective Tissue Disorders, HIV, Drugs, Toxins, Congenital Left-to-Right Shunts, etc.
    Class II: PH with Left Heart Disease
  • Left Atrial or Ventricular Heart Disease
  • Left-sided Valvular Heart Disease
    Class III: PH Associated with Lung Diseases or Chronic Hypoxia
  • COPD, Interstitial Lung Disease, Sleep Disordered Breathing, etc.
    Class IV: PH Due to Chronic Thrombotic and/or Embolic Disease
  • Thromboembolic obstruction of the proximal or distal pulmonary arteries
  • Nonthrombotic obstruction of the pulmonary arteries (ie: tumor, foreign body, etc.)
    Class V: Miscellaneous causes
  • Sarcoidosis, Lymphangiomatosis, etc.

  • Given the numerous potential causes for PH, any patient with suspected PH requires significant investigations to diagnose PH and then to determine the etiology of their PH. This includes basic blood work (looking for evidence of polycythemia), an ECG (evidence of RAE or RVH), a CXR, and echocardiogram, a CT Chest, a V/Q scan (to detect chronic thromboembolic disease), a 6-minute walk test, and a Right-Heart Catheterization to name a few!

    These patients are managed by the multidisciplinary PH team where the goals of treatment include symptom management, improving quality of life, and prolonging survival, which often requires a lung or heart-lung transplant.

    Here is a review article on the mechanisms of PH, and here are the 2009 American College of Cardiology Consensus Guidelines for PH.

    Thursday, July 29, 2010

    TIA Management


    Today we reviewed the approach to a patient presenting with symptoms suggestive of a Transient Ischemic Attack (TIA).

    A TIA is defined as an abrupt focal loss of neurologic function caused by reduction in blood flow that persists less than 24 hours and clears without residual disability.

    Diagnosis is made with a thorough history and physical examination, where the latter can be normal in many patients.

    The patient's risk for progression to stroke can be assessed by the ABCD score, which helps to guide the clinician on the need for admission:

    A: Age - 1-pt if over 60 years old; 0-pt if less than 60
    B: Blood Pressure - 1-pt if SBP greater than 140 OR 1-pt if DBP greater than 90
    C: Clinical symptoms - 2-pts if unilateral weakness; 1-pt if language disturbance but no weakness; 0-pt for other symptoms
    D: Diabetes - 1-pt if patient has diabetes; 0-pt if not
    D: Duration - 2-pts if more than 60 min; 1-pt if 10-59 min; 0-pt if less than 10 min

    Score 0-3: low risk, 2-day stroke risk 1%
    Score 4-5: moderate risk, 2-day stroke risk 4%
    Score 6-7: high risk, 2-day stroke risk 8%

    Low risk patients don't need to be admitted for stroke work-up; however, they do require expedited investigations which sometimes warrant an admission. Moderate risk patients and High risk patients generally warrant an admission and investigations and monitoring for stroke.

    Current Canadian Stroke Guidelines recommend rapid turn around times for investigations in a patient presenting with a TIA. Patients are categorized into Emergent, Urgent, and Semi-urgent; and based on these 3 categories, their stroke work-up is recommended to be performed within the given timeline.

    Emergent: investigations within 24-hrs
    • Symptoms within the previous 24-hrs with 2 or more high-risk clinical features (ABCD criteria)
    • Acute persistent or fluctuating stroke symptoms
    • One positive investigation (evidence of acute infarct on CT/MRI; evidence of carotid artery stenosis > 50%)
    • Other factors based on individual presentation and clinical judgment

    Urgent: investigations within 72-hrs
    • TIA within the previous 72-hrs

    Semi-urgent: investigations within 30-days
    • Does not meet urgent or emergent criteria

    Investigations include standard screening blood work, an assessment by a neurologist or stroke specialist, brain CT or MRI, carotid imaging (doppler, CT angio, or MR angio), and ECG.

    Management should include initiation of an anti-platelet agent, once confirmation that there is no intracranial hemorrhage. If not already on ASA, start with 160-mg followed by 81-mg daily. If failing ASA treatment, then change to either Clopidogrel (load with 300-mg followed by 75-mg daily) or Aggrenox (1-tab BID).

    Those with 70 - 99% blockages in their carotid arteries (matching their TIA symptom pattern)should undergo endarterectomy within 2-weeks.

    If Atrial Fibrillation is discovered the patient should be initiated on anti-coagulation therapy immediately after their event, once an intracranial hemorrhage has been ruled out.

    All modifiable risk factors should be addressed by way of smoking cessation, blood glucose control (HbA1C less than 7%), lipid management (LDL less than 2), and blood pressure reduction (less than 140/90).

    The complete Current Canadian Stroke and TIA guidelines can be found here.

    Friday, July 23, 2010

    Pulmonary-Renal Syndromes

    Yesterday we discussed a case of hemoptysis NYD and today we reviewed an elderly gentleman with acute renal failure who was diagnosed with Goodpasture's syndrome.

    Yesterday's differential diagnosis for hemopytsis included vasculitis. In particular one always needs to consider pulmonary-renal syndromes in the differential for hemoptysis, including Wegener's Granulomatosis (WG) and Goodpasture's syndrome.

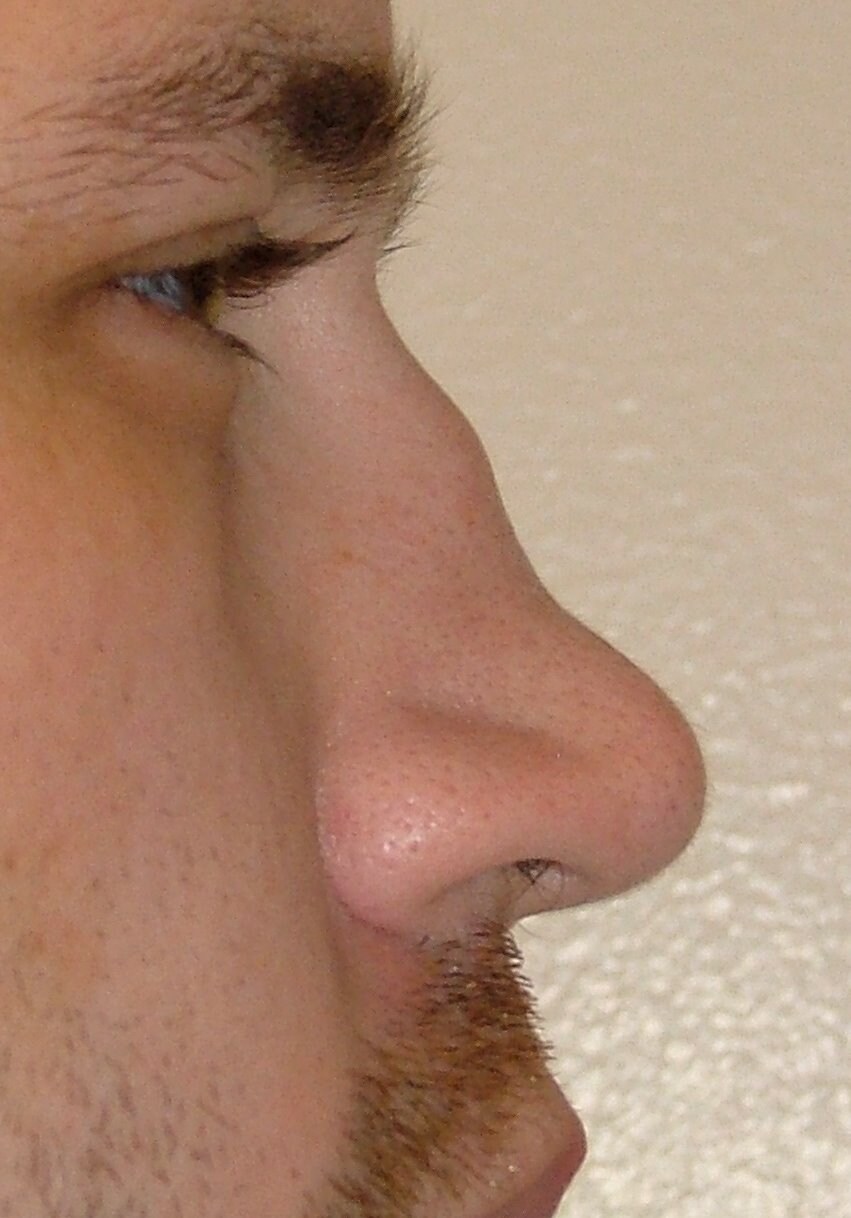
    WG's can present in many ways, but often involves a history or sinusitis or rhinitis, along with constitutional symptoms, hemoptysis, renal failure, and occassionally polyarthralgias. Patients can develop a "saddle nose" due to collapse of their nasal support.

    The pathological triad of WG includes:
    1) systemic necrotizing angiitis
    2) necrotizing granulomatous inflammation of the respiratory tract
    3) necrotizing glomerulonephritis

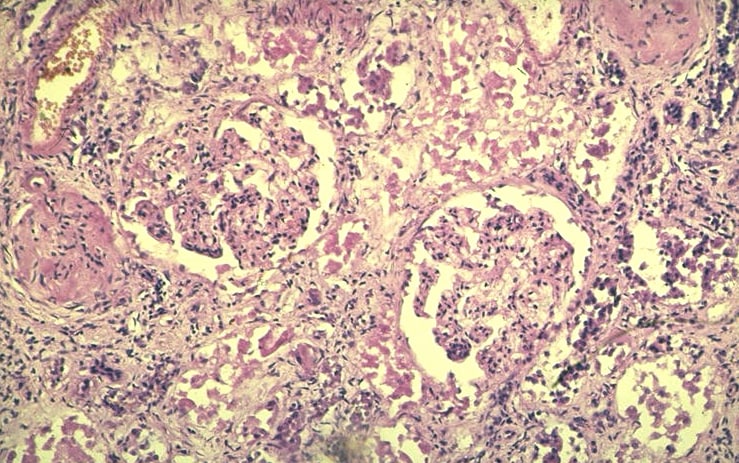
    Diagnosing Wegener's requires a detailed history and physical exam as well as blood work, looking for evidence of c-ANCA or anti-PR3, a urinalysis looking for RBC casts, chest imaging, and often a biopsy of either the kidney or lung. Lung biopsies frequently reveal evidence of vasculitis and granulomatous inflammation. Renal biopsies demonstrate a Pauci Immune picture (i.e.: no deposition of immunoglobulin or complement) with segmental crescentic necrotizing glomerulonephritis.

    Treatment includes pulsed steroids and often cyclophosphamide urgently as this is a rapidly progressive disease. Involvement of a rheumatologist and nephrologist for management and follow-up is usually warranted.

    Goodpasture's disease is a triad of pulmonary hemorrhage, glomerulonephritis (GN), and circulating anti-glomerular basement membrane (anti-GBM) antibodies in the blood. However, not all patients present with the triad, but anti-GBM antibodies is a distinguishing feature of Goodpasture's. Most patients (~60 - 80%) present with both pulmonary and renal disease, 20 -40% have only renal disease, and less than 10% have only pulmonary disease.

    Diagnosis, like WG, involves a thorough history and physical exam as well as blood work looking for anti-GBM antibodies, chest imaging, and usually a renal or lung biopsy. Direct immunofluorescence of the renal biopsy will light up and stain along the basement membrane, reflecting the deposition of IgG.

    Treatment again, requires rapid aggressive management; however, in the setting of Goodpasture's there is a role for plasmapheresis to remove any circulating anti-GBM antibodies. This occurs in conjunction with immunosuppression with pulsed steroids and often cyclophosphamide. Again, consultation with a nephrologist is often warranted!

    Here is a review on the differential diagnosis of hemoptysis and here is a brief case report and review of Goodpasture's from The Lancet.

    Tuesday, July 20, 2010

    Lymphadenopathy


    Today we discussed the unfortunate case of a 25 year old young man presenting with a multitude of complaints, including 4-weeks of right shoulder pain, 8-months of lower back pain, head ache, RUQ pain, dyspnea, non-productive cough, night sweats, and an "intentional" weight loss of ~30 pounds over 2 months. He had recently returned from South America, where he had spent the past few months.


    We generated a broad differential diagnosis for this diffuse constellation of complaints. The 3 main categories we reviewed were:

    1) Neoplasm - hematologic vs. solid organ (ie: testicular, given his gender and age)
    2) Infectious - TB, liver abscess, amoebic infection, liver fluke, malaria, infectious endocarditis
    3) Inflammatory - inflammatory bowel disease, SLE, sarcoidosis

    A CT scan revealed multiple lesions within the liver as well as porta hepatis and para-aortic lymphadenopathy. Large volume lymphadenopathy was also seen in the chest, along with some lytic bone lesions. The clinical picture, along with these imaging findings, raise the most likely diagnosis to lymphoma.

    Lymphomas are a heterogeneous group of cancers arising from the reticuloendothelial and lymphatic systems, which often present as solid tumors of lymphoid cells. Historically lymphomas have been categorized as Hodgkins Lymphoma (HL) or Non-Hodgkin Lymphoma (NHL), but as we learn more and more about these cancers the classifications are constantly being upgraded. Currently lymphomas are still broadly categorized as HL and NHL, with the latter group being further subclassified based on the type of cell from which they originate: B-cell, T-cell, or Natural Killer cell.

    HL results from clonal transformation of cells of B-cell origin, giving rise to the pathognomic Reed-Sternberg cells. The cause is unknown, but genetic susceptibility and environmental associations are thought to play a role. HL is slightly more common in patients with immunosuppression secondary to post-transplant drugs, congenital immunodeficiency, HIV, and autoimmune diseases (SLE, RA, Sjogren's, etc.). Patients often present with painless lymphadenopathy, that can become painful after consumption of alcohol... for no clear reason! Usually the lymphadenopathy arises in one area and spreads in a contiguous manner. The classic "B symptoms" are often described: fever, night sweats, and unintentional weight loss. Diagnosis requires a lymph node core biopsy +/- a fine needle biopsy. Depending on the specific type of HL identify on pathology, and the stage at diagnosis, treatment usually involves chemotherapy +/- radiation therapy, surgery, or stem cell transplant.

    NHL is also a disease of clonal transformation, most often of B-cells, but different subtypes of NHL can develop as a result of clonal transformation of T-cells or Natural Killer cells; classification depends on immunophenotyping, genotyping, and cytogenetics. NHL is much more common than HL. Immunosuppressed patients are also at risk for NHL. The exact etiology of NHL is yet to be discovered, but it is hypothesized that a viral cause may be at play. Patients often present again with painless lymphadenopathy; however, in NHL they can often have multiple areas of involvement. Occasionally patients can present with SVC syndrome secondary to compression of the SVC from nodal enlargement, or acute renal failure secondary to obstruction of the ureters from retroperitoneal or pelvic lymph nodes.

    Diagnosis requires a lymph node core biopsy for nodal architecture as well as immunophenotyping and cytogenetics for subclassification of the lymphoma. Full imaging with CT of the chest/abdo/pelvis and a BM biopsy is required for staging +/- a PET scan (this image shows lymphoma with increased uptake of 18-FDG in the brain, chest, and spleen). Although not fully validated in clinical settings, PET scans can be used in the proper setting, as determined by the oncologist and the radiologist.

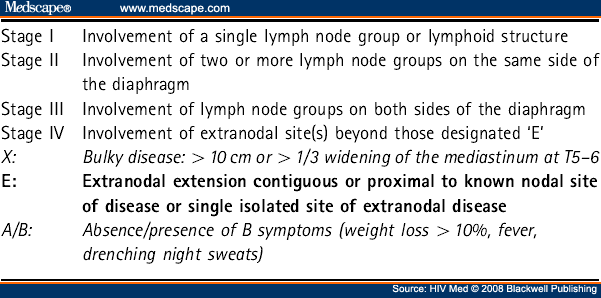
    Staging of NHL follows the Cotswold Modified Ann Arbour Staging. Prognosis is generally better for those with B-cell NHL compared to T-cell NHL. The International Prognostic Index (IPI) is used to help guide clinicians and patients with aggressive lymphomas. There are 5 risk factors with the IPI, and outcomes deteriorate as the number of risk factors increases.

    1) Age over 60

    2) Poor performance status measured by the ECOG (Eastern Cooperative Oncology Group)

    3) Elevated LDH

    4) More than 1 extranodal site

    5) Stage III or IV disease

    Patients in the highest IPI risk group (4-5 risk factors) have a 50% survival rate at 5-years, whereas those in the lowest IPI risk group (no risk factors) have a very high cure rate. Modifications to the IPI have been made to account for diffferent NHL, including the FLIPI (follicular lymphoma) and the R-IPI (diffuse large B-cell lymphoma).

    Treatment for NHL is again specific to the subtype of lymphoma and the stage at diagnosis; however, it generally incorporates chemotherapy "R-CHOP" (rituximab (anti-CD20 monoclonal antibodies), cyclophosphamide, doxorubicin, vincristine, prednisone), radiation therapy, or both +/- stem cell transplantation.

    Here is a great review article on the approach to a patient with lymphadenopathy.

    Friday, July 9, 2010

    Welcome to the Horses & Zebras of TGH

    Welcome to GIM at TGH and this, the official blog of the TGH CMR!

    This is my first posting and I will try to update the blog every few days with summaries from morning report, noon rounds, physical exam rounds, etc. as well as links to articles and web sites that provide excellent reviews of the topics at hand. Today's post will be a brief summary of the past week's salient teaching points!

    Last week we discussed an interesting case of seizure in a patient with a recent history of malaria, travel, and fever. We reviewed the general breakdown of the most common causes of seizure by age category:

    Children:
    -febrile seizure, seizure disorder
    Adults (~20 - 50):
    -trauma, toxic, alcohol withdrawal, metabolic, seizure disorder/idiopathic
    -less likely stroke or tumour
    Older Adults (>50):
    -more likely stroke or tumour
    -could still be one of the other causes


    Last Friday we discussed a great case of HCV cirrhosis and SBP, spontaneous bacterial peritonitis. Here is a NEJM review article on the management of cirrhosis and ascites. There is also a very helpful video on NEJM demonstrating how to perform a paracentesis found here. And this all links in well with Physical Exam Rounds yesterday, where we examined a patient with ascites. You should all have received the JAMA Rational Clinical Exam paper entitled "Does this patient have ascites?" in your inbox (it is not possible to link to the website!). Key points to remember for physical examination of ascites:
    1) Most sensitive findings are ANKLE EDEMA and INCREASED GIRTH
    2) Most specific finding is FLUID WAVE


    During our Emergency Lecture Series we have had a variety of excellent topics covered, including a review of atrial and ventricular arrhythmias. Here you will find the 2006 ACC/AHA guidelines for patients with Atrial Fibrillation as well as the 2003 guidelines for patients with SVT. Here you will find the ACC Pocket Guide for ventricular arrhythmias. And on that note, here is a link to drugs that can induce Torsades de Pointes.


    Today's Morning Report discussed a fascinating case of SOB, muscle weakness, swollen joints, and weight loss. The patient was found to have an elevated CK and a small pericardial efffusion on 2D Echo, but normal inflammatory markers (ESR and CRP). There were no sensory findings and only mild objective muscle weakness on exam.

    During our discussion the topic of Constrictive Pericarditis came up and how to make the diagnosis; which requires a right and left heart catheterization to compare pressures across the septum. Constrictive pericarditis is a relatively rare diagnosis that is often caused by tuberculosis or other infections agents such as fungi and parasites. Here is a great article, as mentioned in Morning Report, describing a case of constrictive pericarditis!

    For our case, there is no diagnosis as of yet - hopefully Team 5 will keep us all posted! However, as we discussed, our differential for this case includes (but is not limited to):

    1. Malignancy with associated Polymyositis/Dermatomyositis
    2. Rheumatoid arthritis
    3. Inclusion body polymyositis
    4. Mixed connective tissue disorder

    Dermatomyositis (DM) is less likely given that the patient has no skin manifestations. The classic skin features of DM include:

    Gottron's papules: lacy, pink/violaceous, raised or macular lesions, symmetric over the dorsal interphalangeal joints, elbows, and knees
    Heliotrope rash: a violaceous discolouration of the eyelids with periorbital edema
    Shawl sign/V-sign: erythematous rash over the shoulders/neck (in the pattern of a shawl) OR neck/chest (V-sign)
    Periungual telangiectasias: nail changes (cuticular hypertrophy) with or without Raynaud's
    Mechanic's hands: coarse, fissured, scaly, hyperkeratotic hands

    Thanks to former CMR David Frost for the DM links! For a complete review of DM please see this great review article in American Family Physician and a previous Blog by David Frost.

    Monday, June 28, 2010

    Signing off...


    This is the last blog post of the year for me...


    I've enjoyed managing the TWH Tangents and TGH Horses and Zebras Blogs for 2009-2010. I hope you found them helpful


    Your CMR 2009-2010

    Monday, June 14, 2010

    Pancytopenia


    Today we discussed an approach to the patient with pancytopenia

    This is an indication for a bone marrow aspirate and biopsy, which usually shows increased or decreased marrow cells:

    Hypocellular marrow
    -Marrow toxins: May be dose-dependent, predictable as with chemotherapeutic agents, immunomodulators (methotrexate, cyclophosphamide, etc) or idiosyncratic (chloramphenicol, sulfa drugs, phenytoin, many others); radiation, EtOH
    -Infection: Parvovirus B12, EBV, HIV, HHV-6, viral hepatitis; severe sepsis
    -Immune: SLE, RA (rare), graft-versus-host
    -PNH
    -Idiopathic stem cell failure

    Hypercellular marrow
    -MDS, leukemias, lymphomas, myeloma
    -Nutritional- severe megaloblastic anemia (B12, folate)
    -Marrow replacement/infiltration: myelophthisic anemia , myelofibrosis, granulomatous disease (TB, sarcoid, fungal), solid tumor metastases (prostate and breast are most common)

    The topic of the MGUS and multiple myeloma 'spectrum' came up. Here are some helpful criteria based on the NEJM review paper cited below:

    MGUS
    Marrow plasma cells less than 10% and M-protein (in blood) less than 30g/L
    No clinical manifestations

    Smouldering MM
    Marrow plasma cells at least 10% and/or M-protein at least 30g/L
    No clinical manifestations

    Multiple myeloma
    Marrow plasma cells over 10% and/or M-protein at least 30g/L
    Clinical features of hypercalcemia, renal failure, anemia, bone lesions, infections, plasmacytomas

    Waldenstrom's macroglobulinemia
    Marrow plasma cells over 10% and M-protein over 30 (IgM)
    Clinical features of anemia, bleeding, organomegaly, IgM immunoglobulin

    Primary amyloidosis (AL)
    Marrow plasma cells less than 10% and M-protein less than 30
    Clinical fearures of fatigue, wt loss, purpura, nephrotic syndrome, CHF, neuropathy, orthostatic hypotension, massive hepatomegaly

    Links:
    Click here for a "medical mystery" from NEJM on panyctopenia
    Click here for an excellent review paper on MGUS/myeloma differentiation

    Saturday, June 12, 2010

    Eating disorders- medical complications


    Today we discussed the medical complications of eating disorders, which can be devastating and affect any system, with mortality as high as 10% in anorexia and 2% in bulemia. A few points:


    Electrolyte/renal abnormalities
    -Hypokalemia (may be from vomiting, diuretic abuse, laxative abuse)
    -Metabolic alkalosis (volume depletion, diuretics)
    -Hyponatremia (diuretics, polydipsia prior to weighings)
    -Hypophosphatemia
    -Hypomagnesemia
    -Chronic kidney disease (may be contributed to by nephrocalcinosis, tubular dysfunction)

    Cardiovascular
    -Bradycardia (may or may not be secondary to electrolyte abnormalities)
    -Cardiomyopathy (potentially reversible)
    -Long QT
    -Mitral valve prolapse

    GI
    -Parotic hypertrophy
    -Decreased contractility
    -Mallory-Weiss teats
    -SMA syndrome
    -Gallstones

    Endocrine
    -Amenorrhea
    -'Sick euthyroid' syndrome
    -Growth retardation
    -Hypoglycemia

    Skeletal
    -Osteopenia/osteoporosis

    Hematologic
    -Marrow suppression

    Neurologic
    -Seizures
    -Peripheral neuropathy

    Dermatologic
    -Lanugo hair
    -Hair loss
    -Yellow/orange skin- hypercarotenema
    -Russell sign (callus over knuckles)
    -Edema

    Refeeding syndrome: When pts become rapidly "anabolic" after prolonged periods of starvation, severe electolyte abnormalities can develop and must be aggressively replaced.
    -Hypophosphatemia
    -Hypokalemia
    -Hypoglycemia
    -Edema

    Link:
    Click here for a NEJM review of anorexia
    Click here for a case report of reversible severe cardiomyopathy from anorexia

    Tuesday, June 8, 2010

    Status Epilepticus


    Today we discussed an approach to status epilepticus and seizures in general.

    Defined as continuous or repeated seizures without return to baseline for 20-30min (brain activity; may not have convulsions).
    NB- there is a movement to make the time part of this definition much shorter (to 5 minutes)

    Most seizures last 1-2 min. You need to intervene if beyond this point. At 20 min, the seizure per se damages the brain (scarring, self-perpetuating as sz focus). Also treat if series of short sz with incomplete recovery in between.

    Approach is to treat the seizure AND look for the underlying cause

    Acute causes: bleed, stroke, trauma, metabolic (e.g. hypoglycemia, hyponatremia, hypocalcemia, others), infections (esp. CNS), hypoxia, intoxication/drugs (or withdrawal), major organ faiure (uremia, hepatic failure)
    Chronic: mass, non-compliance with meds

    Complications of sz: aspiration, orthopedic complications, lactic acidosis, rhabdomyolysis

    Practical approach:

    ABC- clear the airway (do NOT put anything in the pt's mouth to prevent 'tongue biting, etc), roll on side, ensure breathing (apply O2)
    Get monitors- Vitals, O2 sat,
    IV access
    CHECK THE GLUCOSE!, If low, amp of D50, glucagon 1mg IM if no IV
    Thiamine 100mg IV (esp. if EtOH, pregnant, cancer pts)
    Blood: CBC, lytes, renal, Ca profile, glucose, transaminases, drug levels, tox screen

    If no immediately reversible cause (e.g. hypoglycemia), drugs to use acutely:

    Benzos- lorazepam IV 12-24h anti-sz effect. Loraz 0.1mg/kg at 1-2mg/min (usually 1-2mg aIV at a time, repeated to max) This will stop 80% of sz.
    May give diazepam PR if no IV access. 0.2mg/kg PR x 1 or midazolam 5mg IM x1

    Phenytoin (Dilantin) 20mg/kg IV load at 50mg/min (e.g. 1400mg over 30 min in 70kg)
    If needed, give further 5-10mg/kg.
    A couple of points about phenytoin for status:
    Do not mix phenytoin and D5; it crystallizes, which is not very helpful in status epilepticus.
    Never give dilantin and dopamine together; can cause profound hypotension for unclear reason

    Phenobarbital: Strongly consider intubation here
    20mg/kg IV @50-75mg/min. This pt should be in ICU

    Others: Propofol infusion, midazolam infusion

    Look for underlying- bloodwork, CT, LP if fever.
    Mimics of status: myoclonus, rigors, movement disorders, herniation (early)

    Link:

    Click here for an excellent review of status epilepticus from Chest (yes, a weird place for it to be)


    Thursday, June 3, 2010

    Endocarditis


    Today we discussed endocarditis. This is a very important topic to have knowledge of regardless of what area one practices in, both in terms of suspecting and confirming the diagnosis, and proper management. The natural history of untreated endocarditis is 100% mortality. A few points:

    Traditional breakdown is by time course; perhaps less relevant today than previously.

    Subacute classically presents as a chronic, wasting illness, with fever, wt loss and progressive heart failure and complications as the heart is progressively damaged over weeks to months. Typical organisms are (in order) viridans group streptococci, enterococcus, st. aureus

    Acute presents with rapidly progressive valvular destruction over days, often with catastrophic hemodynamic and other complications. Typical organisms are st. aureus, enterococci, viridans group streptococci, HACEK organisms.

    Other useful classifications that help with predicting microbiology and complications are native vs. prosthetic valve and R-sided vs. L-sided.

    Some physical findings (not exhaustive!)

    Signs of valvular involvement or local complications:
    -murmurs (esp. AI, MR, TR)
    -signs of L or R-sided heart failure
    -bradycardia (heart block can occur from paravalvular abscess)

    Signs of embolic complications/phenomena and vasculitis
    -any focal neurological deficit
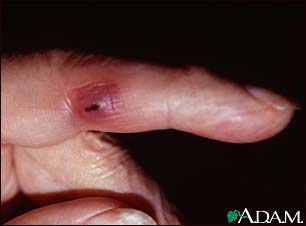
    -peripheral cutaneous signs: Splinter hemorrhages, Osler nodes, Janeway lesions, Roth spots, clubbing, subconjuntival and other mucosal petechiae. Remember to look for these on the feet too
    -splenomegaly

    Signs of underlying causes
    -track marks for IDU
    -oral exam for dental hygiene

    Diagnosis:
    -multiple blood cultures from different sites off antibiotics are KEY to the diagnosis and management

    Modified Duke's criteria can be helpful (see link for full details):

    Major
    -multiple blood cultures consistent or Q-fever serology +ve
    -echo consistent (oscillating mass, abscess, dehiscence of prosthesis)
    -new murmur

    Minor
    -predisposing heart condition or IVDU
    -fever
    -vascular phenomena (emboli, etc as above)
    -immunologic phenomena (as above)
    -blood cultures not meeting criteria for "major"

    Definite: (2 major) or (1 major+3 minor) or (5 minor)
    Possible: (1 major and 1 minor) or (3 minor)

    ECG- check for new blocks (esp. 1st degree AVB; suggests abscess)

    Therapy
    General principles- need cidal antibiotic. Generally need minimum 4-6 wks of IV therapy

    Indications for valve replacement (NB- surgery is probably under-utilized)
    -CHF as a direct consequence
    -Severe valvular insufficiency
    -Paravalvular abscess
    -Embolic phenomena post-initiation of therapy
    -Persistently positive cultures or fever despite adequate medical therapy
    -Size of vegetation (relative)

    Links:
    Click here for the complete modified Duke's criteria
    Click here for a review article from NEJM

    Monday, May 31, 2010

    Paroxysmal Nocturnal Hemoglobinuria


    Today we discussed a very rare cause of anemia and thrombosis, PNH.

    This disease results from an acquired mutation in DNA encoding components of complement system, which leads to several clinical manifestations:

    1) Hemolysis, which is episodic ("paroxysmal"). The degree of hemolysis depends on how many RBCs are abnormal. Unclear why it is sometimes nocturnal, as shown above. Chronic hemolysis can cause severe anemia, and renal failure from myoglobin-induced tubular damage

    2) Thrombosis. It is unclear why patients with PNH are hypercoagulable; it may have to do with platelet abnormalities in PNH (all hematopoietic stem cells can be involved). Thrombosis is usually venous, but can be arterial. The hallmark is thromboses in relatively unusual places, most commonly portal vein or other intra-abdominal veins and cerebral venous sinus thrombosis.

    3) Diminished hematopoiesis. Because marrow stem cells are involved, pancytopenia can be ther presenting manifestation.

    Diagnosis: "PNH assay", which is flow cytometry for the clone of cells with abnormal complement-related proteins.

    Therapy:

    1) For hemolysis:
    -supportive measures include transfusion, iron supplementation, folic acid supplementation.
    -specific therapy is Eculizumab, a monoclonal antibody that inhibits complement activation, and significantly reduces hemolysis. Limiting factor is cost, estimated at $400,000 / year

    2) For thrombosis:
    -anticoagulation with heparin then warfarin as secondary prevention
    -there may be lower risks of thrombosis on Eculizumab
    -there is retrospective evidence supporting prophylactic anticoagulation with warfarin in selected patients

    Stem cell transplant is also an option reserved as a last resort

    Links:
    Click here for the paper showing the effect of Eculizumab in PNH

    Thursday, May 20, 2010

    Cocaine- medical complications


    Today we discussed cocaine intoxication. Some points:

    Acute intoxication:
    Cocaine is a sympathomimetic, and acute intoxication presents with this toxidrome:
    Hypertension, tachycardia, fever, flushing, diaphoresis, mydriasis, altered mental status, possibly seizures

    The anticholinergic toxidrome presents very similarly. The 2 can be distinguished by:
    -diaphoresis in sympathomimetic (vs. 'dry as a bone' in anticholinergic)
    -more prominent hypertension in sympathomimetic

    Management:
    Besides the specific organ issues discussed below, general managment consists of
    -benzodiazepines (mainstay!)
    -if BP control is required, DO NOT USE PURE BETA BLOCKERS; this causes unopposed alpha agonism and makes hypertension/vascular effects worse; labetalol is safe in this situation (because it is both alpha and beta-blocker), and phentolamine or phenoxybenzamine are alpha-blockers that can be used.

    Common specific organ effects (besides acute intoxication):
    CNS- cerebral vasoconstriction, including stroke; movement disorders
    CV- coronary vasospasm, which may cause MI; tachyarrhythmias, hypertensive urgency/emergency
    Resp- perforated septum, smoking cocaine causes SOB, wheezing, chest pain hemoptysis in a large proportion of users. Acute fever, dyspnea, hypoxia, infiltrates soon after smoking has been called "crack lung"; is from alveolar damage. Interstitial lung disease is possible.

    Recently recognized complication:
    In the past year or so, there have been many recognized cases (including at this hospital) of patients presenting with agranulocytosis from cocaine "contaminated" with levamisole, an anti-helminth drug used in animals.

    Click
    here for a summary of this complication
    Click here for a paper from the Annals of Internal Medicine describing this. CMAJ has a similar report.